Sensitivity vs Specificity: Work a USMLE 2×2 Table
Learn sensitivity vs specificity with a worked USMLE 2×2 table, predictive values, prevalence, likelihood ratios, cutoff changes, and ROC interpretation.
Sensitivity asks: **Among people who have the disease, how many test positive?** Specificity asks: **Among people who do not have the disease, how many test negative?** In a diagnostic 2×2 table, both use disease-status columns as denominators; predictive values instead use test-result rows—a distinction reflected in the FDA’s definitions of diagnostic test performance.
That denominator choice explains why a test can have high sensitivity and specificity yet give a positive result that is more likely false than true. Work through the original example below to connect the arithmetic to the clinical question.
Sensitivity vs Specificity: Build the 2×2 Table
Suppose researchers evaluate a hypothetical blood test in **1,000 people**. An independent reference standard establishes that 100 have the target disease and 900 do not. The blood test is positive in 90 diseased people and 90 nondiseased people.
These are invented teaching data, not performance estimates for a real assay.
| Test result | Disease present | Disease absent | Row total | |---|---:|---:|---:| | Positive | 90 true positives (TP) | 90 false positives (FP) | 180 | | Negative | 10 false negatives (FN) | 810 true negatives (TN) | 820 | | Column total | 100 | 900 | 1,000 |
“True” and “false” describe agreement with the reference disease status. “Positive” and “negative” describe the test result. A false positive therefore belongs in the **positive-test, disease-absent** cell—not in the disease-present column.
The reference standard matters: agreement between two tests is not automatically proof of diagnostic accuracy. The FDA’s diagnostic-study guidance distinguishes sensitivity and specificity against a reference standard from measures of agreement against a non-reference comparator.
Choose the Denominator Before Calculating

Each metric answers a different conditional question. The group named after “among” supplies the denominator. The definitions below follow the CDC’s diagnostic sensitivity and specificity teaching resource and the National Academies’ explanation of predictive values.
| Metric | Question being answered | Formula | Worked result | |---|---|---|---:| | Sensitivity | Among diseased people, how many test positive? | TP / (TP + FN) | 90 / 100 = **90%** | | Specificity | Among nondiseased people, how many test negative? | TN / (TN + FP) | 810 / 900 = **90%** | | Positive predictive value (PPV) | Among positive tests, how many have disease? | TP / (TP + FP) | 90 / 180 = **50%** | | Negative predictive value (NPV) | Among negative tests, how many lack disease? | TN / (TN + FN) | 810 / 820 ≈ **98.8%** | | Prevalence | Among everyone tested, how many have disease? | (TP + FN) / total | 100 / 1,000 = **10%** |
Notice the reversal: sensitivity starts with known disease and asks about the result; PPV starts with the result and asks about disease. **P(positive test given disease) is not P(disease given a positive test).**
In this example, 90% sensitivity does not mean that a positive patient has a 90% chance of disease. Exactly half the positive results are false positives.
Why Prevalence Changes Predictive Values
Now apply the same hypothetical test—still 90% sensitive and 90% specific—to 1,000 people in a population with **1% prevalence**.
Only 10 have disease. Nine test positive and one tests negative. Of the 990 without disease, 99 test positive and 891 test negative.
| Population | True positives | False positives | PPV | NPV | |---|---:|---:|---:|---:| | 10% prevalence | 90 | 90 | 90 / 180 = **50%** | 810 / 820 ≈ **98.8%** | | 1% prevalence | 9 | 99 | 9 / 108 ≈ **8.3%** | 891 / 892 ≈ **99.9%** |
The false-positive **rate** stays at 10%, but it acts on a much larger nondiseased group. False positives therefore outnumber true positives eleven to one in the lower-prevalence population.
Holding sensitivity and specificity constant, increasing prevalence increases PPV and decreases NPV; decreasing prevalence does the reverse. The National Cancer Institute’s screening-methods primer explains this dependence of predictive values on prevalence.
The key qualifier is **holding test performance constant**. Sensitivity and specificity do not contain prevalence directly in their formulas, but real populations may differ in disease severity, competing diagnoses, or other features that change measured performance. A large empirical analysis of diagnostic-accuracy studies found associations between prevalence and estimated sensitivity and specificity. For a clean calculation, use the stated values; clinically, check whether those values apply to the patient population.
Likelihood Ratios Convert Pretest Into Posttest Odds
Predictive values describe results in a specified population. Likelihood ratios provide another route: start with a patient’s pretest probability, then update it using the observed result.
The formulas are:
- **LR+ = sensitivity / (1 − specificity)**
- **LR− = (1 − sensitivity) / specificity**
For our 90%-sensitive, 90%-specific test:
- LR+ = 0.90 / 0.10 = **9**
- LR− = 0.10 / 0.90 ≈ **0.111**
A positive result is nine times as likely in someone with disease as in someone without it. A negative result is about one ninth as likely in someone with disease as in someone without it. These definitions and the odds-update relationship are detailed in the AHRQ guide to test-performance metrics.
Work the Probability–Odds–Probability Sequence
Do not multiply a probability directly by a likelihood ratio. Use this sequence:
- **Pretest odds = probability / (1 − probability)**
- **Posttest odds = pretest odds × LR**
- **Posttest probability = odds / (1 + odds)**
The Clinical Methods chapter on diagnostic testing describes this application of Bayes’ theorem.
With a 10% pretest probability and a positive result:
- Pretest odds = 0.10 / 0.90 = 1/9.
- Posttest odds = (1/9) × 9 = 1.
- Posttest probability = 1 / 2 = **50%**.
This reproduces the PPV from our original table.
With the same pretest probability and a negative result, posttest odds are (1/9) × (1/9) = 1/81. The posttest probability of **disease** is 1/82, or approximately **1.2%**. Its complement is the NPV: approximately **98.8%**.
An LR of 1 leaves the odds unchanged. LR+ values around 10 or greater and LR− values around 0.1 or lower are conventional markers of substantial evidence, not automatic treatment thresholds, as the AHRQ methods guide emphasizes.
Cutoff Changes Trade False Negatives for False Positives
Assume a continuous marker is called positive when its value is **at or above** a cutoff.
Lowering that cutoff makes more results positive. It can convert false negatives into true positives, increasing sensitivity, but also convert true negatives into false positives, decreasing specificity. Raising the cutoff reverses the tradeoff. These changes may occur in steps in a finite dataset rather than with every tiny adjustment, as illustrated by the National Academies’ discussion of ROC thresholds.
| Cutoff change | More results become | Sensitivity | Specificity | Main tradeoff | |---|---|---|---|---| | Lower cutoff | Positive | Increases or stays unchanged | Decreases or stays unchanged | Fewer false negatives, more false positives | | Raise cutoff | Negative | Decreases or stays unchanged | Increases or stays unchanged | Fewer false positives, more false negatives |
The direction depends on the positivity rule. If **low** marker values indicate disease, “lower cutoff means higher sensitivity” is not a universal rule. First identify which side of the threshold is positive.
The familiar **SnNout** and **SpPin** shortcuts also need qualification. High sensitivity favors a useful negative result, and high specificity favors a useful positive result, but the actual probability change depends on both test characteristics through the likelihood ratio and on the starting probability. That follows from the AHRQ likelihood-ratio framework.
ROC Curves Show Performance Across Cutoffs
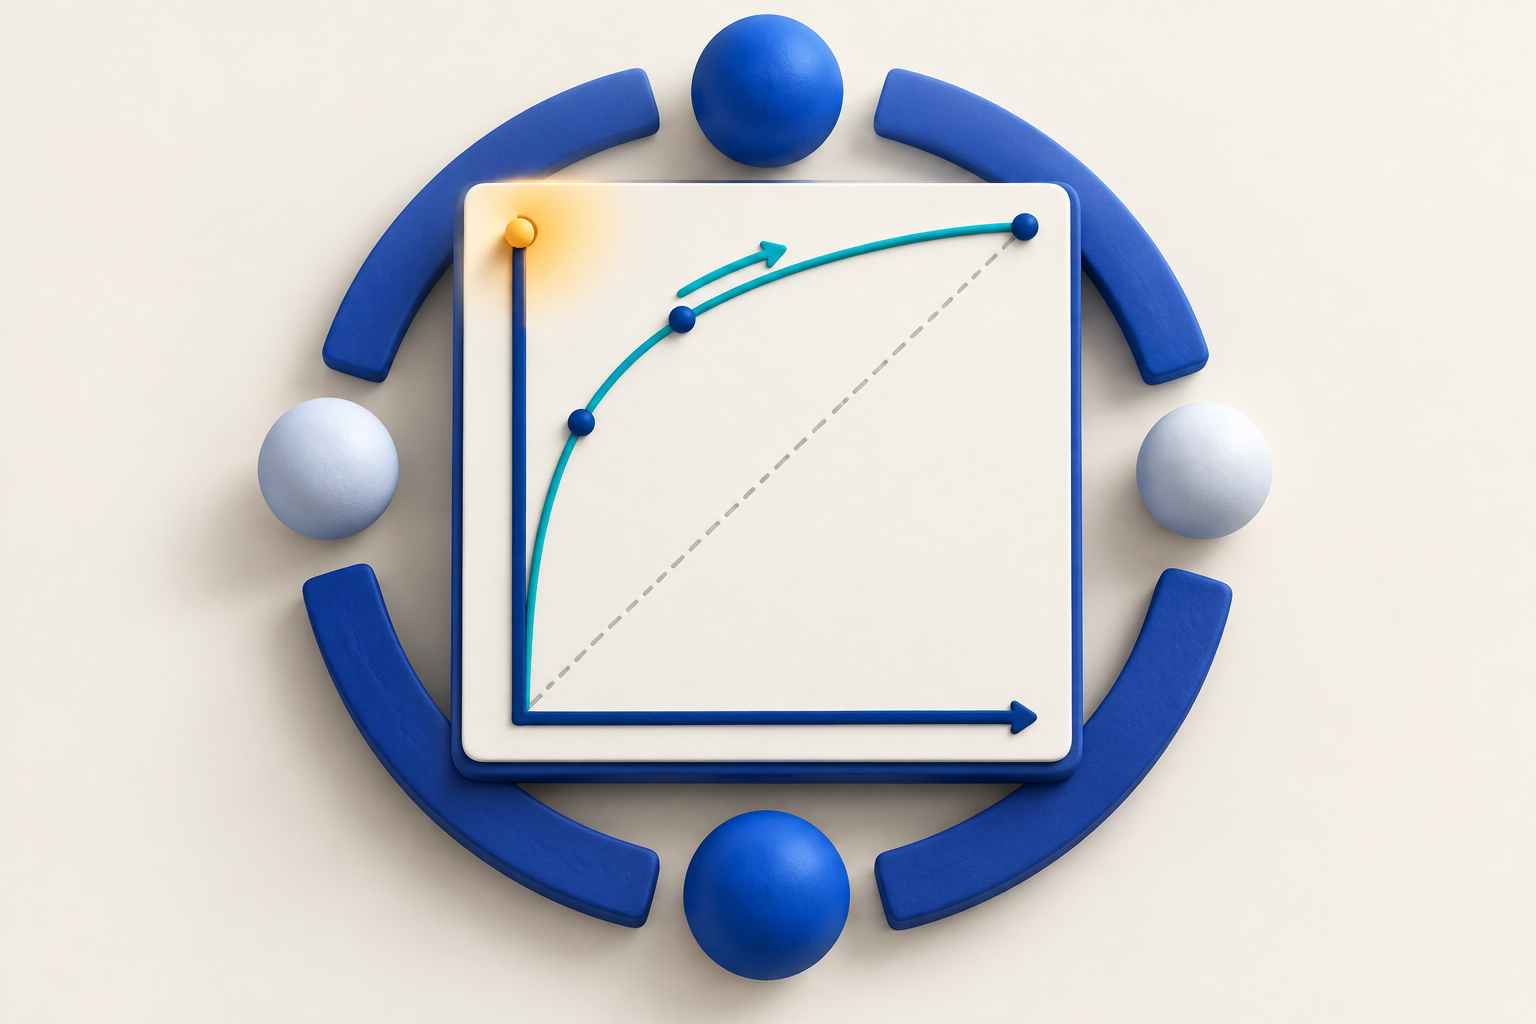
A receiver operating characteristic curve plots:
- **Y-axis:** sensitivity, or true-positive rate.
- **X-axis:** 1 − specificity, or false-positive rate.
Each point represents performance at a particular threshold. For a higher-is-positive marker, lowering the threshold generally moves the operating point upward and rightward: more diseased people are detected, but more nondiseased people test positive. The upper-left corner combines high sensitivity with a low false-positive rate. These relationships are described in the National Academies’ ROC analysis chapter.
Area under the curve summarizes discrimination across thresholds: **AUC = 1** represents perfect discrimination, while **AUC = 0.5** represents chance-level discrimination. AUC does not supply the PPV for a particular patient or select the clinically appropriate cutoff by itself; prevalence and the consequences of errors still matter. The AHRQ methods guide explains the distinction between threshold-based performance and predictive values.
Original Vignette: A Positive Result in a Low-Risk Population
A hypothetical screening assay is evaluated against a reference standard in 10,000 adults. Disease is present in 1% of participants. The assay has 90% sensitivity and 95% specificity. An adult from this population tests positive. Assuming no additional risk information, what is the probability that the adult has the disease?
**A. 1% · B. 15.4% · C. 90% · D. 95%**
**Answer: B, approximately 15.4%.**
There are 100 diseased adults, producing 90 true positives. There are 9,900 nondiseased adults, producing 495 false positives because the false-positive rate is 5%.
**PPV = 90 / (90 + 495) = 90 / 585 ≈ 15.4%.**
The decisive clue is that disease probability is requested **after a positive result**. That selects the positive-test row, not the disease-present column. The nearest distractor, 90%, is sensitivity: it answers how often diseased adults test positive, not how often positive adults have disease. The 95% option makes the same error with specificity.
As a cross-check, LR+ = 0.90 / 0.05 = 18. Pretest odds are 1/99; posttest odds are 18/99. Converting back gives 18/117 = 15.4%. Even this strong likelihood ratio does not overcome the very low starting probability enough to make disease more likely than not.
Final Takeaways
- **Sensitivity and specificity use disease-status denominators; PPV and NPV use test-result denominators.**
- With fixed sensitivity and specificity, higher prevalence raises PPV and lowers NPV.
- Likelihood ratios multiply **odds**, not probabilities; convert before and after updating.
- Cutoff direction depends on which marker values count as positive. ROC curves plot sensitivity against **1 − specificity**.
For related epidemiology explanations, continue through the CoreStepPrep core concepts. Put the denominator distinction into practice: Try a free USMLE question at CoreStepPrep.
Sources and further reading
- www.fda.gov/regulatory-information/search-fda-guidance-documents/statistical-guidance-reporting-results-studies-evaluating-diagnostic-tests-guidance-industry-and-fda
- www.cdc.gov/labtraining/docs/job_aids/additional_resources/sensitivity_and_specificity_final_5_23_2022_508.pdf
- www.ncbi.nlm.nih.gov/books/NBK605677
- www.ncbi.nlm.nih.gov/books/NBK550207
- pubmed.ncbi.nlm.nih.gov/37460126
- www.ncbi.nlm.nih.gov/books/NBK98249
- www.ncbi.nlm.nih.gov/books/NBK383
- www.ncbi.nlm.nih.gov/books/NBK22319